
Few medications have had a scientific afterlife as unusual as sildenafil.
Originally developed as a potential treatment for angina, sildenafil was famously repurposed for erectile dysfunction and later approved for pulmonary arterial hypertension.
But its story may not end there.
Over the past decade, sildenafil and other phosphodiesterase type 5 (PDE5) inhibitors have become the center of a fascinating—and at times contradictory—oncology debate.
Does sildenafil increase cancer risk, suppress cancer growth, or somehow have different effects depending on the tumor?
The answer is not as simple as “yes” or “no.” Early observational studies raised concerns about melanoma, while laboratory, genetic, and clinical research has increasingly suggested that PDE5 inhibition may have anticancer and immune-modulating effects in certain malignancies.
The result is a compelling example of why biological plausibility, epidemiologic association, and true causation are not always the same thing.
Sildenafil inhibits phosphodiesterase type 5 (PDE5), an enzyme responsible for breaking down cyclic guanosine monophosphate, or cGMP.
Normally, nitric oxide stimulates the production of cGMP within smooth muscle. Increased cGMP promotes smooth-muscle relaxation and vasodilation.
Nitric oxide → ↑ cGMP → smooth-muscle relaxation → vasodilation
PDE5 normally limits this pathway by degrading cGMP. Sildenafil blocks PDE5, allowing cGMP concentrations to remain elevated for longer.
PDE5 inhibition → ↓ cGMP breakdown → prolonged cGMP signaling
That mechanism explains sildenafil’s effects in erectile dysfunction and pulmonary hypertension. But PDE5 signaling also exists in other tissues—including certain immune and tumor-related pathways—which is where the cancer story becomes considerably more complicated.
The concern did not initially come from epidemiology. It began with molecular biology.
Melanoma frequently involves activation of the RAS/RAF/MAPK/ERK signaling pathway, which promotes tumor-cell proliferation and survival.
Experimental research showed that activation of BRAF, a major driver mutation in melanoma, could reduce expression of the PDE5A enzyme.
Lower PDE5A activity was associated experimentally with increased melanoma-cell invasiveness.
This led researchers to ask an obvious and potentially alarming question:
If melanoma cells become more invasive when PDE5A activity decreases, could a medication designed to inhibit PDE5 have a similar effect?
It was a biologically plausible hypothesis—but biological plausibility alone does not prove that a medication causes cancer in humans.
In 2014, researchers analyzing participants in the Health Professionals Follow-up Study reported that recent sildenafil use was associated with an increased incidence of melanoma.
The reported hazard ratio was approximately 1.84, meaning recent sildenafil users appeared to have nearly twice the relative risk of developing melanoma compared with nonusers in that analysis.
The study, published by Li and colleagues in JAMA Internal Medicine, attracted substantial attention because it appeared to connect the earlier laboratory observations with disease occurring in real people.
A large Swedish nested case-control study published the following year also detected an association, although the magnitude was considerably smaller. The reported odds ratio was approximately 1.21.
Several subsequent meta-analyses likewise reported a modest statistical association between PDE5 inhibitor exposure and melanoma, generally in the range of roughly a 10–15% relative increase.
At first glance, the pattern looked concerning.
But then researchers looked more closely at how that association behaved.
Finding an association between a medication and cancer does not automatically mean the medication caused the cancer.
Researchers therefore began looking for patterns expected if sildenafil were genuinely promoting melanoma.
Several expected patterns were missing.
One of the classic clues supporting causation is a biological gradient: greater exposure should generally produce greater risk.
For example, if a medication truly promotes carcinogenesis, people exposed repeatedly or for longer periods might reasonably be expected to experience greater risk than people exposed only once.
That pattern was not observed consistently with PDE5 inhibitors.
In the Swedish study, men receiving only a single prescription demonstrated the strongest association, while men receiving multiple prescriptions did not show a progressively increasing risk.
More sildenafil did not consistently equal more melanoma.
That substantially weakens the argument for a direct carcinogenic effect.
Another unusual finding was that the association appeared concentrated primarily in melanoma in situ and stage I disease.
A convincing signal was not seen for more advanced stage II–IV melanoma.
If PDE5 inhibition were making melanoma biologically more aggressive, researchers might expect an association with invasive or advanced disease.
Instead, the pattern looked more consistent with increased detection of early lesions.
A large United Kingdom cohort study involving more than 145,000 men exposed to PDE5 inhibitors provided another important piece of the puzzle.
Researchers found that PDE5 inhibitor users were not only more likely to be diagnosed with melanoma. They were also more likely to develop basal cell carcinoma and solar keratosis.
Those conditions are strongly associated with ultraviolet exposure, yet there is no convincing biological reason that PDE5 inhibition should independently cause all of them.
The common denominator may not have been sildenafil. It may have been the sun.
This introduces one of epidemiology’s most important concepts: confounding.
People who use erectile-dysfunction medications may differ systematically from people who do not. Some observational datasets suggest PDE5 inhibitor users may, on average, have socioeconomic and lifestyle characteristics associated with more recreational sun exposure, travel, outdoor leisure activity, access to healthcare, and dermatologic screening.
Those factors could increase both UV exposure and the likelihood that an early melanoma is discovered.
The apparent relationship could therefore look something like this:
Lifestyle and socioeconomic factors → greater sun exposure + greater healthcare surveillance → more early melanoma detected
In that scenario, sildenafil use becomes a marker associated with another risk factor rather than the biological cause of melanoma itself.
A later analysis assessing the relationship against established criteria for causation concluded that the epidemiologic evidence did not convincingly support PDE5 inhibitors as a cause of melanoma.
Long-term animal carcinogenicity studies included in sildenafil regulatory data have also not demonstrated a clear carcinogenic effect.
While epidemiologists were trying to determine whether sildenafil increased melanoma risk, cancer researchers studying the immune system began observing something almost opposite.
In certain experimental models, PDE5 inhibition appeared to suppress rather than promote tumor progression.
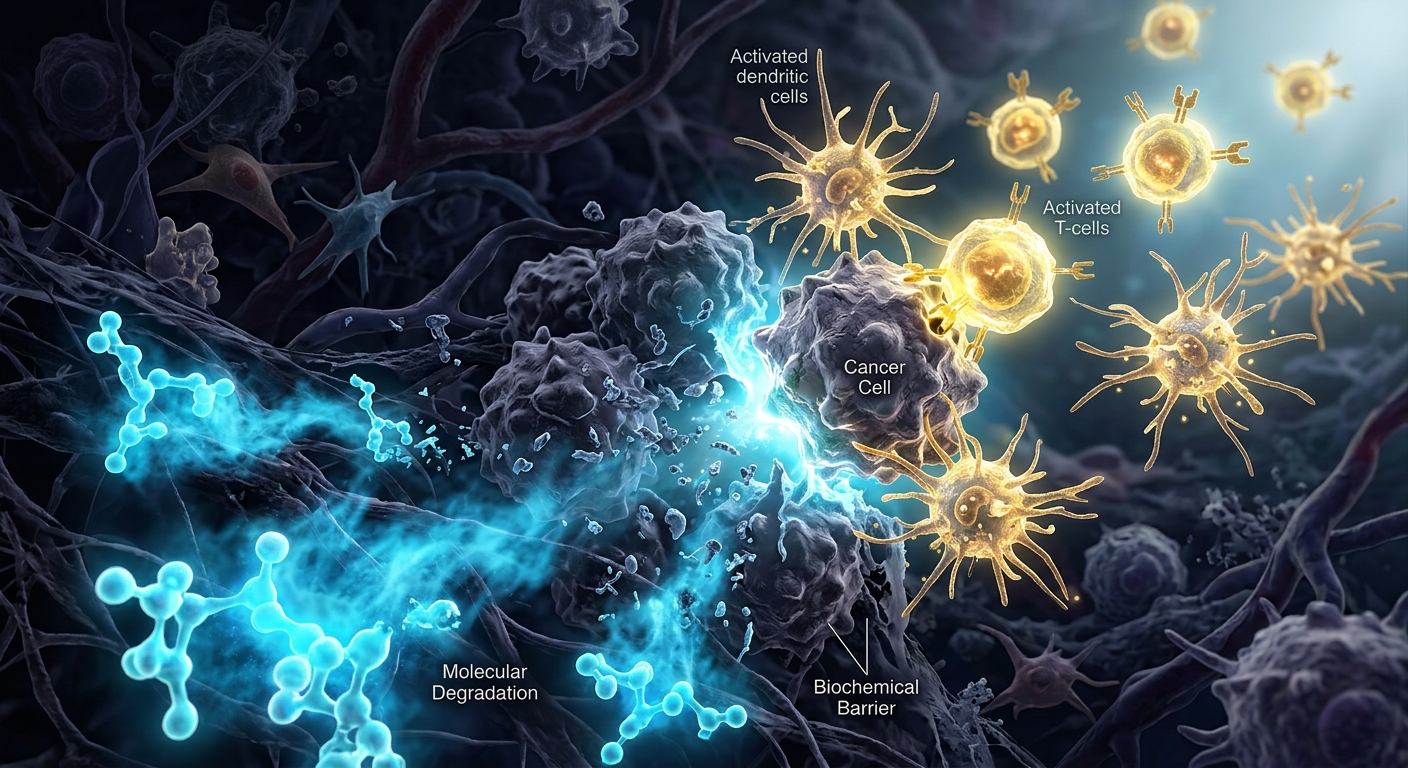
One reason involves a group of immune cells known as myeloid-derived suppressor cells (MDSCs).
The immune system is capable of recognizing and destroying abnormal cells. Tumors, however, develop mechanisms that suppress that response.
MDSCs are among the cells tumors can recruit to create an immunosuppressive microenvironment.
These cells can express enzymes and signaling molecules—including arginase 1 and inducible nitric oxide synthase (iNOS)—that interfere with T-cell activity.
Tumor → activation of suppressive myeloid cells → ↓ T-cell function → reduced antitumor immunity
In other words, tumors can effectively place a biochemical brake on immune cells that might otherwise attack them.
A landmark study published by Serafini and colleagues in the Journal of Experimental Medicine in 2006 found that PDE5 inhibition could reduce the immunosuppressive activity of MDSCs.
Sildenafil reduced expression of arginase 1 and iNOS, improved antitumor T-cell responses, and delayed tumor growth in several mouse models.
Researchers also observed restoration of T-cell proliferation in laboratory experiments involving blood from patients with conditions including multiple myeloma and head-and-neck cancer.
The proposed pathway was almost the reverse of the original melanoma concern:
PDE5 inhibition → ↓ myeloid-derived immune suppression → ↑ T-cell activity → stronger antitumor immune response
This raised an intriguing possibility: a familiar medication developed for vascular disease might eventually be repurposed as an adjunct to cancer therapy.
The anticancer hypothesis did not remain confined to laboratory mice.
A Swedish observational study published in Nature Communications in 2020 examined men with colorectal cancer who used PDE5 inhibitors after their cancer diagnosis.
Post-diagnostic PDE5 inhibitor use was associated with an approximately 31% lower risk of metastasis and an approximately 39% lower risk of colorectal cancer-specific death.
The apparent association was especially notable among patients who had undergone open surgery.
That observation generated another mechanistic hypothesis.
Major surgery can temporarily create a state of systemic inflammation and immune suppression. If PDE5 inhibition helps counter some of that immunosuppression, it might theoretically reduce the ability of residual cancer cells to establish metastatic disease during a vulnerable postoperative period.
Importantly, however, this was an observational association. It cannot prove that sildenafil itself prevented metastasis or cancer death.
More recent research has expanded the proposed immune effects of PDE5 inhibition beyond myeloid-derived suppressor cells.
Dendritic cells play a central role in antitumor immunity. They capture tumor-associated antigens, migrate to lymphoid tissue, and present those antigens to T cells.
This essentially allows dendritic cells to show the adaptive immune system what it needs to attack.
Tumor antigen → dendritic cell → T-cell activation → antitumor immune response
Research published in Nature in 2025 reported that sildenafil could restore impaired dendritic-cell motility in experimental tumor models, improving antitumor immune responses.
When PDE5 inhibition was combined experimentally with anti-PD-1 immune checkpoint therapy, responses improved substantially in mouse models that otherwise demonstrated treatment resistance.
This is particularly intriguing because checkpoint inhibitors depend on a functioning antitumor immune response. If PDE5 inhibition can improve the movement or function of immune cells required to initiate that response, it could potentially make resistant tumors more responsive to immunotherapy.
But there is an important distinction:
A therapy that works dramatically in mice is not automatically an effective cancer treatment in humans.
Controlled clinical trials are necessary before these findings can alter routine cancer treatment.
The potential cancer effects of PDE5 inhibition may extend beyond immunity.
Research reported in 2026 proposed another mechanism involving intracellular cholesterol trafficking.
Cancer cells require cholesterol for membrane formation, signaling, proliferation, and other metabolic processes involved in tumor growth.
Experimental PDE5 inhibition was reported to interfere with normal cholesterol handling by causing cholesterol to become trapped within lysosomal compartments.
PDE5 inhibition → altered lysosomal cholesterol trafficking → reduced cholesterol availability to tumor cells → impaired metastatic potential
The study also reported additive effects when PDE5 inhibition was combined with statins, medications that reduce endogenous cholesterol synthesis.
This creates a particularly interesting therapeutic concept: attacking a tumor’s cholesterol supply from two different directions.
Statin → ↓ cholesterol synthesis
PDE5 inhibition → altered cholesterol trafficking
Combined effect → potentially greater metabolic pressure on cancer cells
As with the immune findings, this remains an emerging research area and should not be interpreted as evidence that sildenafil or statins should be self-administered as cancer treatment.
Another approach researchers have used is Mendelian randomization.
This method uses naturally occurring genetic variants as proxies for long-term biological exposure to investigate whether modifying a particular molecular target is likely to influence disease risk.
A 2025 drug-target Mendelian randomization analysis reported that genetically proxied PDE5 inhibition was associated with a lower risk of colorectal and gastric cancers.
These findings do not prove that taking sildenafil will prevent gastrointestinal cancer. Genetic proxy studies estimate the consequences of long-term modification of a biological pathway, which is not identical to taking a medication intermittently.
Nevertheless, they provide another independent line of evidence supporting continued investigation of PDE5 as an oncology target.
The most scientifically accurate answer is:
Current evidence does not support a simple universal effect of sildenafil on cancer.
| Question | What the Evidence Suggests |
|---|---|
| Does sildenafil cause melanoma? | Observational studies found a small association, but lack of dose-response, concentration in early-stage disease, and associations with other sun-related conditions argue against a clear causal relationship. |
| Is sildenafil a proven carcinogen? | No convincing evidence currently establishes sildenafil as a human carcinogen. |
| Can PDE5 inhibition affect tumor biology? | Yes. Experimental research suggests effects on immune suppression, dendritic-cell function, tumor metabolism, and other pathways. |
| Can sildenafil prevent cancer? | Not established. |
| Can sildenafil treat cancer? | Not as a standard cancer therapy. Most anticancer evidence remains experimental or observational. |
| Could PDE5 inhibitors eventually become oncology drugs? | Possibly. Drug-repurposing research is actively exploring this possibility. |
The sildenafil story illustrates a broader lesson in medical science.
Observational studies can identify important safety signals, but an association alone cannot tell us whether one factor caused another.
Researchers must ask whether the association demonstrates a dose-response relationship, whether there is a plausible biological mechanism, whether alternative explanations exist, whether the finding is reproducible, and whether experimental evidence supports the same conclusion.
With sildenafil and melanoma, the initial signal was provocative. But as additional evidence accumulated, confounding from sun exposure, socioeconomic factors, and increased medical surveillance became increasingly plausible explanations.
At the same time, completely different lines of research revealed that the same molecular target might influence tumor immunity, metastasis, and cancer metabolism.
The same drug can intersect with different biological pathways in dramatically different ways.
Drug repurposing is attractive in oncology because medications such as sildenafil are already widely used and have well-characterized pharmacology and safety profiles.
If researchers eventually demonstrate that PDE5 inhibitors improve cancer outcomes when combined with surgery, chemotherapy, immunotherapy, or other treatments, development could potentially move more rapidly than it would for an entirely new molecule.
But promising mechanisms are not enough.
The crucial unanswered question is whether these intriguing laboratory and observational findings will translate into meaningful improvements in human cancer survival, recurrence, or treatment response in randomized clinical trials.
Current evidence does not establish sildenafil or other PDE5 inhibitors as a cause of melanoma. The modest association detected in some observational studies appears increasingly compatible with confounding factors—particularly differences in sun exposure and melanoma detection—rather than a direct carcinogenic effect.
That does not make sun protection any less important. Patients should continue appropriate UV protection and skin surveillance according to their individual risk factors regardless of whether they use sildenafil.
At the opposite end of the spectrum, sildenafil should also not be considered an established cancer treatment. The potential anticancer effects of PDE5 inhibition remain an active field of research, with some of the most compelling findings still coming from animal models, mechanistic studies, observational cohorts, and genetic analyses.
For now, sildenafil occupies an unusual scientific position: a medication once investigated for the heart, transformed into one of the world’s best-known treatments for erectile dysfunction, and now being investigated again—this time as a possible tool for manipulating the tumor microenvironment.
The “little blue pill” is not a proven cause of cancer—and it is not yet a cancer drug. But its most unexpected chapter may still be ahead.
Medical disclaimer: This article is intended for educational purposes only and does not constitute medical advice. Sildenafil and other PDE5 inhibitors should be used only for appropriate medical indications under the guidance of a qualified healthcare professional. They should not be started, stopped, or used as cancer therapy based on preclinical or observational research.
